• Skip to primary navigation
  • Skip to main content
  • Skip to primary sidebar

Hip and Knee News

News Resource About Hip, Knee and Orthopedic Surgery

  • Home
  • Hip Surgery
  • Knee Surgery
  • Resources
    • Hip and Knee Glossary
  • About/Contact

Blog

10 Things to Know About Knee Replacement Surgery

by

What are the “top ten things” I should know about knee replacement surgery?

10 Things to Know About Knee Replacement SurgeryThe following points apply to knee replacement surgery, no matter what implants are used, or how skilled your surgeon is.

Knee surgery is not always the best option for knee pain or issues with walking.

Please keep in mind the following:

  • Minimally invasive or not, knee surgery is painful. AVOID surgery if you can.
  • Results from knee replacement depend critically on YOUR motivation, commitment, and participation.
  • Proper PREPARATION for knee replacement will improve your outcome.
  • Artificial knees can be NOISY; they sometimes pop, click, and clunk during movement.
  • SWELLING, ACHING, and HEAT continue for longer than most people expect.
  • Full recovery from knee replacement takes LONGER than most people think.
  • Physical, family, emotional, and spiritual SUPPORT will help recovery after knee replacement.
  • OLDER patients with knee arthritis will typically recover faster than younger patients; while this makes no sense, it is usually the case.
  • If you cannot EXERCISE before and after surgery, avoid knee replacement surgery.

Filed Under: KNEE, Knee Surgery Tagged With: after, complication, recovery, risk

About Knee Replacement

by

Knee Replacement FAQ

It’s important to understand the reasoning, procedure, and options behind a knee replacement. Here are some of the most frequent questions that patients ask.

Is knee arthroplasty different from knee replacement?

No. The terms can be used interchangeably. Total knee replacement is also called total knee arthroplasty. Similarly, a partial knee replacement is called uni-compartmental knee arthroplasty.

Is knee replacement surgery a fairly routine operation?

photo of knee surgeryYes. Hundreds of thousands of knees are replaced each year in the U.S., and world demand for knee replacements is increasing as people live longer and want more out of their lives.

Most orthopedic surgeons perform hundreds of knee replacements each year. While routine, knee replacement is still serious surgery. Each patient is unique, and each person’s anatomy demands careful attention to detail and precise steps during surgery.

Will a new knee joint be a perfect substitute for the real knee?

No, and you should be skeptical of any doctor or advertisement telling you otherwise. Those advertisements are designed to make a sale, rather than educate and enlighten consumers.

Normal human knee movement consists of gliding, rotation, sliding, and other complex movements. A synthetic joint can only approximate the intricacy and complexity of the knee joint that you were born with. No artificial knee joint, regardless of manufacturer’s advertising claims, or surgeon claims, has ever duplicated the complexity and intricate movements of the natural human knee.

The human knee joint has major ligaments and other soft tissue supports; these have fine nerve endings that send sensory, positional, and perceptual feedback to the brain from the knee. An artificial knee is simply metal and plastic. For severely diseased knees, modern total knee replacements provide excellent pain relief and function, but they are never a perfect substitute for the real thing.

What does an artificial knee feel like, if it does not feel natural?

Replacing your natural knee joint is a bit like replacing your natural teeth with dentures. Your own teeth are more than mechanical devices; they play a complex role in biting, chewing, hot-cold sensation, positional sense, vibration, and even taste.

Dentures are not natural or normal; they lack nerve endings and cannot feel vibration, heat, cold, touch, or any of the things we take for granted with our natural teeth. That is why dentures are useful only for patients whose own teeth are decayed or destroyed. Similarly, knee replacements are useful for patients with severe cartilage destruction, who have no other options, and who have thoroughly explored the possibilities.

How can I increase my chances of a successful knee replacement?

The success of knee surgery depends on your participation and how your body heals. Any operation on the human body has some uncertainty with respect to the outcome, despite the best of care.

Healing is a complex process, and each person heals differently. Knowledge and a strong partnership with your medical team leads to greater success, and makes it easier to work through any unexpected outcomes. The purpose of this website is to bridge the information gap and help you understand what questions to ask.

Can arthritis occur in a knee that is replaced?

No. Since cartilage is replaced by metal and plastic during knee replacement, there is no cartilage left in the knee to deteriorate. However, arthritis is a complex disease that frequently affects surrounding tissues, such as muscles, nerves, ligaments, and the synovial lining of the joint. This is one reason why despite a successful knee replacement, some pain, stiffness, and swelling may persist for many months.

In some patients, arthritis in other joints, such as the back and hip, can contribute to continuing symptoms after surgery. This is an important point to understand. Not all knee pain is from the knee; some may be coming from a diseased hip or spine, or other systemic illness like fibromyalgia or rheumatoid arthritis.

Stiff muscles, tendons, and ligaments can take many months to return to normal, even after healing from a knee replacement.

How long is the recovery after a total knee replacement?

Most patients are happy, mobile, and about 70 to 80 percent recovered by one month. Individual medical conditions such as diabetes, smoking, advanced age, obesity, neuropathy, heart and lung disease, Parkinson’s disease, and related variables can change recovery time drastically.

About 80 to 90 percent of the recovery is complete by six to eight weeks, but some aches and stiffness can persist for many months. The last 5 percent to 10 percent of soreness, achiness, and stiffness can take a year or two to subside completely.

For most patients, the most significant part of the recovery takes place during the first month. But keep in mind that patient variability is great; there is no value in comparing yourself with anyone else. Each person has a unique recovery.

Is recovery from knee surgery faster for younger patients?

No, and you should know about this paradox. Experience shows that the best recovery from knee replacement is in older patients, who have severe arthritis, and who have tried all reasonable conservative means of treating pain before surgery.

Younger patients, especially those of male gender and muscular physique, generally tend to have a noticeably slower recovery and higher level of pain from any knee surgery. This may reflect different expectations, different pain tolerances, body image, hypersensitivity of younger tissues, and other variables, but it is a fact that the younger patient should approach knee replacement surgery with added caution.

What is the best age for knee replacement surgery?

The optimal range is late 50s to late 70s. Most knee arthritis affects this age group, and a properly implanted total knee replacement should last the rest of life in such patients.

Should I get a second opinion before knee surgery?

Yes. If you have unanswered questions or doubts, additional opinions are always a good idea. A wealth of information exists on reputable websites. You can also learn a lot from orthopaedic implant companies as well as from friends, family, and others who have had knee surgery.

It is best to explore all your options and make your decision accordingly. Treat all information with a healthy dose of skepticism; any credible resource should be able to answer your questions to your satisfaction, no matter how authoritative or influential that resource holds itself to be.

A surgeon replaced my knee, and it did not work well. Can anything be done?

Usually, yes. Knee replacement surgery can be complicated by subtle infection, implant mal-positioning, and other unexpected outcomes that can leave patients unhappy. If this is the case, you should always seek a second opinion, even if a doctor has told you that nothing can be done. A variety of complex factors can compromise the results of knee replacements; fortunately, most such problems can be resolved.

Filed Under: KNEE, Knee Surgery Tagged With: arthroplasty, knee joint, knee replacement

Life with an Artificial Hip

by

Living with your new artificial hip

Medical advances have made living with an artificial hip a remarkably pain-free and effective solution to hip joint problems for most.

How long will the artificial hip last?

Life with an Artificial HipIn most cases, the hip replacement should outlast your lifespan. The 15-to-20-year data on the longevity of hip replacement components is excellent, with more than 90 percent of the implants still functioning well in many studies. But, this is neither a guarantee nor assurance, for the simple reason that life is unpredictable.

Many factors affect the future of a hip replacement or resurfacing, such as accidents, fractures, late infections, and deterioration in your overall health. How well you take care of yourself down the road is something the surgeon cannot control.

The longevity of a hip replacement thus depends on many factors, including the following:

  • Surgeon skill in implanting the components
  • Known history or track record of the implants
  • How well you take care of yourself and your health
  • Understanding and respecting the limitations of a prosthetic lifestyle
  • Your activity level and body weight
  • Avoiding high-impact or extreme sports

How do I know if I have a metal allergy to the hip part?

Orthopaedic implants are made of alloys of cobalt-chrome and titanium that have been implanted in millions of patients over the past several decades. Most instances of a persistently painful hip after replacement have to do with a problem related to the surgery, or possibly an infection. A true metal allergy is extremely rare, and seldom encountered in clinical medicine.

What will weather changes feel like in the hip?

Some patients report increased pain and stiffness, or can feel changes in the weather after hip surgery. These sensations are not common though, and usually will disappear over 1 to 2 years after surgery. For the first couple years, the bone adapts and grows around the metal prosthesis, and this bone activity probably leads to sensitivity to weather and pressure changes.

How about future dental work and other surgery?

Because you have an artificial hip joint in place, you must take care to protect it from infection. The same applies to any artificial implant in your body. Before having dental work (teeth cleaning, fillings, extraction or root canals) or certain medical procedures (colonoscopy, biopsy, endoscopies, etc.), you must take an antibiotic.

The antibiotic will help prevent bacteria from getting into the blood stream and thus into your hip. The odds of this happening are very rare, but the antibiotic can reduce this already small risk.

For routine dental prophylaxis following hip replacement surgery, antibiotics are recommended for your lifetime after the surgery.

In what other situations will I need antibiotics after the hip replacement?

Antibiotics given for other medical procedures may vary. Contact your physician for advice if there is any doubt. Antibiotics are needed if you develop an infection such as an abscessed tooth, pneumonia, bronchitis, and skin or urinary infections.

If you have a cut anywhere that develops an infection, conditions like a tooth abscess or ingrown toenail developing, seek medical attention urgently. Ignoring a festering sore means that there is a risk the bacteria could migrate to the hip, resulting in a serious deep infection, even though it happens rarely.

Will the new hip set off a metal detector at the airport?

Most likely, it will. Tell airport personnel that you have an artificial joint prior to entering the metal detector. Metal detection sensitivity at airports is highly variable, and it is impossible to say if a certain detector will set off the equipment. Your surgeon will supply you with an implant identification card that you can carry to prove that you have metal hip replacement parts.

Can I have a MRI scan after hip replacement?

Yes. MRI scans of other parts of your body are safe after hip replacement. Although some old MRI scanning equipment may not be compatible with your prosthesis, the majority of MRI scanning equipment today is safe and compatible with hip replacement parts. You may also have a CT scan of any part of your body after a hip replacement.

How will I know if my hip implants are recalled?

In the extremely unlikely event of a recalled implant, you will be contacted by the company who made the device. All implants have lot numbers registered with the implant maker. This information is kept in your medical record. If you want a copy of your X-ray or exact implant type and model for your records, please let your medical team know.

Rest assured that of the millions of artificial joints implanted each year, the incidence of recall is exceedingly rare. Implant companies monitor the performance of their products very carefully.

Is there a long-term risk of failure of hip implants?

Implants are engineered to withstand your body weight and activity level, but the moving parts of a hip replacement do wear over a period of several decades. A properly aligned hip replacement done by a competent, experienced surgeon will usually last the lifetime of most patients.

Subtle component mal-positioning and suboptimal orientation can however compromise the lifespan of the implant. This is why the skill and expertise with which the hip is implanted in your body is a critical determinant of durability.

Filed Under: HIP, hip surgery Tagged With: metal detector, mri, recall, risk

After Hip Surgery

by

Recovering from Hip Surgery

What happens after hip surgery? Here are answers to commonly asked questions.

What can I expect during the hospital stay?

You can expect to see several people who will help with your recovery. A physical therapist will assist with hip exercises and walking. An occupational therapist will assist you with learning everyday activities, such as dressing and bathing, while your hip is healing. Your surgeon, his associates, medical doctors, and nursing staff will see you daily. A nursing assistant will help with bathing and activities that you are unable to do yourself.

The first night or two may be hard considering that you will have an unfamiliar bed, diet, and medications. Ask for a sleeping pill or anti-anxiety medication if that will help. Anticipate several weeks before your normal sleeping, eating, and resting patterns are restored.

How long will I stay in the hospital?

The average hospital stay after hip replacement is one or two days. The day after your surgery, you will be helped into a chair and you may be able to walk limited distances. Your activity will increase with each day that follows.

Recovery time varies from one patient to another. Much depends on other existing medical conditions. For example, arthritic disease in other major joints, heart disease, diabetes, obesity, depression, and other related conditions will affect recovery.

Most people return to their own place of residence after a hip replacement. Some elderly or debilitated patients may need to go to a nursing home to recuperate.

Preventing blood clots

What measures are taken to reduce the risk of blood clots?

For routine hip surgery, it’s common to use a blood-thinning medicine for about 4 weeks after surgery. In addition to a blood thinner, doctors also use early mobility, spinal anesthesia, leg exercises, foot pumps, and efficient surgery as adjunctive measures to minimize the risk of blood clots.

Why is a blood thinner needed after surgery?

This is to reduce the risk of a blood clot. Hip surgery is associated with a risk of blood clots developing in the calf, thigh, or pelvic veins. These clots often do not have any obvious symptoms or signs. Clots can cause chronic swelling of the legs, pain, and circulation and skin problems. In rare instances, a clot can break off and travel to the lungs, which can sometimes be fatal. This is why blood clots and blood-thinning medications are taken so seriously.

The risk of clots greatly decreases when the blood is thinned after surgery. Therefore, we use a blood thinner in every patient following hip surgery.

If you have ever had a blood clot before, or have ever had an adverse reaction to a blood thinner, please let your physician know so that he or she can plan an accordingly.

Common sensations

What sensations can I expect right after surgery?

Typically, patients have little to no pain, but nausea is more common. This nausea can come from the anesthetic drugs or from pain medicines and we can help control it by changing pain medicines and prescribing anti-nausea agents if necessary. If you have pain, nausea, or any other disagreeable sensation, let the nursing staff know. They are very knowledgeable in controlling such symptoms. Usually, an adjustment of medications is all that it takes to address any disagreeable sensations.

Why do I have a popping sensation in the new hip?

This can happen from a tendon, called the psoas tendon, rubbing against the new hip. With exercise and time, this sensation will disappear, assuming that it ever manifests in the first place. Usually this popping sensation occurs while the hip is healing, and while turning the leg side to side.

Why is the outside of my thigh numb?

This is normal after most anterior approaches to hip replacement or hip resurfacing. The incision cuts small nerve fibers that run from inside to outside of the hip, so the skin to the outside of the cut always feels numb after hip surgery. Usually, this sensation will resolve over time and is not a major problem for patients. Most patients will not notice that the outside of the scar feels numb.

Is it normal for the muscles to spasm and tighten after surgery?

Yes. Sometimes unexpected spasms of the leg muscles occur after surgery, usually as the person is healing from the operation. These spasms will go away. If they are particularly troublesome, your doctor can prescribe a muscle relaxant medicine, which can help.

Why are my appetite, mood, food-taste, and sleep different after surgery?

Altered appetite, bowel habits, depression, and mood swings are common after hip replacement. This is very important to know, understand, and anticipate. In some cases, medications might be necessary to control such symptoms.

All surgery elicits powerful psycho-social and physiological responses, which vary from one person to another. These responses are normal,; your medical team will help you get through them. It takes time for the body, mind, and soul to recover from any invasive operation.

Caring for your incision

Should I keep the incision covered?

Yes. Covering daily with a gauze dressing is best. You can shower with the dressing on, protecting it as much as possible, and then changing with a new dressing after the daily shower. Avoid touching the incision; the skin around the scar should be kept clean with soap and water. No antibiotic ointments are necessary.

Alternatively, you can remove the dressing, wash around the incision with soap and water, pat dry, and cover with a new dressing. Showering is safe at any time after surgery, but immersing the incision in a bathtub should wait until the stitches/staples are removed.

Can I put any lotion on the scar?

While stitches or staples are still in, avoid applying anything to the incision; simply keep it clean and dry. Once stitches or staples are out, you can use Vitamin E cream to massage and loosen the scar. Massaging the thigh area with an anti-inflammatory or cortisone cream can reduce skin inflammation and tenderness; many such ointments are available over the counter.

What if I am allergic to the adhesive used in the dressing?

If your skin cannot handle the adhesive or tape, or if there is drainage from the incision, a useful tip is to use feminine hygiene pads as a dressing. These are self-adhesive, comfortable, very gentle on the skin, and very absorbent.

Who will remove stitches and when?

Usually the home health nurse will remove stitches or staples, no earlier than 21 days after surgery. In some cases, the stitches may be left in longer, depending on the rate of healing. Home health nurses should take a digital photo of the incision if there is a concern and send it to your physician via e-mail.

When can I shower, take a bath, or swim?

Shower anytime after the surgery, if you can sit or stand safely with help. The incision can be covered with a plastic wrap. A new, dry dressing should be used to cover the incision after the shower.

Tub baths and immersion into water, such as a swimming pool, should be delayed until the stitches or staples are out and the skin has sealed completely. This takes at least a couple of weeks after surgery.

Swelling

How long will I have swelling and warmth in the surgical site?

Swelling and warmth around the scar are common after a hip replacement or hip resurfacing operation. The ankle may also swell on the operated leg. This represents the normal process of healing and can last for several weeks to months, depending on factors such as circulation, body weight, diabetes, and other variables.

Obesity, diabetes, poor circulation, poor muscles, varicose veins, high activity, heart disease, and swelling before surgery will usually result in a longer period of swelling and heat in the operated leg. Elevating your leg at night and wearing compression stockings during the day will help.

Deep aches and swelling in the hip can persist for a long time because bone, a living tissue, continues to re-model and adapt around the metal implants. This increased metabolic activity can lead to lingering soreness and swelling after heavy activity, all of which will disappear with time.

When can I stop wearing the compression stockings after hip replacement?

Compression stockings may be applied to both legs after surgery to control swelling, and many patients inquire when these can be discontinued. The answer is that if swelling is not a concern, you can stop wearing the stockings at any time.

These stockings are prescribed to control one of the most common nuisances after any hip operation, namely, swelling in the leg and ankle. The stockings have nothing to do with preventing blood clots; for that problem, it’s common to use a blood thinner and other strategies discussed here.

Preventing infection

How do you prevent infections during hip replacement?

Some of the key factors in reducing the risk of infection involve scrubbing of the skin with an antiseptic, antibiotics given before surgery, surgeon experience, a team-approach designed to promote efficiency, and standardized protocols. It is impossible to completely eliminate this risk, but it’s possible to get the risk down to nearly zero. It is very rare to have an infection after routine hip replacement. .

Is there a long-term risk of infection in an artificial hip?

Yes, there is a lifetime risk of infection with any artificial implant in your body, whether a hip joint, heart valve, or other synthetic component. As long as you maintain good health and appropriate body weight, avoid smoking, maintain proper hygiene, keep diabetes under control, and promptly address even minor infections in your body, the risk of infecting an otherwise well-functioning hip implant is essentially zero.

What if an infection does develop?

An early infection shows up as redness and pain around the healing incision. This can generally be treated with oral antibiotics alone, usually taken for 5 to 10 days. Very rarely, the hip joint has to be opened and washed out to clean the tissues and effectively treat an early infection.

A late infection that happens months or years after surgery is more serious, and will require additional surgery. Such infections occur because the immune system can be weakened by age, infirmity, tobacco use, heavy alcohol use, cancer, and other conditions.

In these cases, the infected prosthesis is removed and a temporary antibiotic-loaded hip is implanted. After three or more months, a new hip joint is implanted. Six weeks of antibiotics and these two operations will effectively treat an established deep infection in the hip. Fortunately, such cases are very rare, and late deep infections usually occur in immune-compromised patients with other serious medical problems.

Leaving the hospital

How will I manage at home?

After Hip SurgeryIf help from an adult family member or friend is not possible, it may be necessary to stay at an inpatient rehabilitation facility. You will not be able to drive for the first couple of weeks after surgery. If you go home, a home health agency will check on you at home, about three times a week or more, to help with walking, exercise, incision checks, medications, and communication with the doctor.

The home health agency will send a nurse to do blood draws and follow-up care, a physical therapist to continue therapy, and possibly an occupational therapist. The nurse also communicates with your physician to keep them updated on your progress.

How is my hospital discharge handled?

Typically, a social worker will visit with you after surgery and work with the therapists and nurses to formulate a discharge plan. The social worker will assist in coordinating discharge to your home, a skilled nursing facility, in-patient rehabilitation facility, or nursing home.

What determines when I can go home after hip replacement?

You can go home when you can ambulate safely with a walker, go up and down stairs, and get to the bathroom. Typically, you will have had a bowel movement before discharge, and will be able to take a shower. Your doctor is the one making the ultimate decision about the safety and timing of your discharge. You will need someone to drive you home from the hospital.

When must I come back for a visit after hip surgery?

You will return for a visit about one month after surgery; call or e-mail if you have questions before that time. This guide and your home health nurse can be helpful resources. Long-distance patients may use email, sending digital photos of their incisions and digital X-rays; this works very well and saves time and travel expense.

When should seek medical help?

Contact your doctor if you have any of the following:

  • persistent drainage from your incision;
  • excessive redness around the incision;
  • increase in the incision pain;
  • increased leg swelling;
  • pain and swelling in the calf of the leg;
  • temperature above 101 degrees;
  • numbness or tingling down the back of the operative leg;
  • chest tightness;
  • new cough;
  • difficulty breathing;
  • or any related concern.

Your family doctor is a good resource if you develop a cold, flu, nausea, vomiting, diarrhea, or constipation. If you are unsure, please contact your surgeon. If unable to reach a doctor, and you feel there is a problem, please go to the local emergency room.

Getting moving

Can I place full weight on the operated leg after surgery?

Yes. But, use some form of assistive device for at least a month after surgery, to avoid a sudden twist and fall. Hip implants are loaded in torsion (a rotational stress is placed on the implant each time you get up, turn in bed, or go up or down stairs), as well as loaded in compression (your weight pressing down). Putting full weight on your hip right after surgery is never a problem.

About a month after surgery, if you feel confident and balanced, you can walk without a cane, but if there is any question, stay with a cane until you feel safe.

In complex, repeat hip implant surgery, these instructions will be more specific to each unique situation. In almost all cases, however, at 12 weeks after such surgery, patients can resume all activities.

Can I kneel down after hip replacement surgery?

Yes. As soon as you’re comfortable, kneeling is safe, as is crossing our legs and lifting weights by bending the knees or back. It is not possible to damage the implants.

How soon can I drive after surgery?

With a left hip replacement, an automatic transmission, and a healthy right leg, you can drive any time after surgery that you are comfortable. Typically this time is about two weeks from surgery, but sometimes longer.

If the right leg is operated on, you can drive in 3 to 4 weeks after surgery. If you feel sleepy or sedated because of pain medications, then you should avoid driving until you are alert and can concentrate on driving.

How much therapy will I need?

You need approximately four weeks of therapy, usually at home, with a visiting home health nurse. Some patients need therapy after this four-week period, and others are already independent. If you need outpatient therapy, usually 4 to 6 weeks will suffice. Once you learn basic hip exercises, you will be able to do them at home.

How much movement can I expect in the new hip?

The amount of movement you achieve should be close to that of a normal hip. That said, existing scar tissue, contractures of the hip joint, severity of arthritis, pain tolerance, motivation for exercise, body size, and other variables profoundly affect how much mobility a person will get. For most patients, the amount of hip movement gained after replacement allows them to engage in all activities of daily life.

Should I exercise after hip replacement?

Yes. A regular program of light aerobic exercise is beneficial from many standpoints, and will optimize the outcome of your hip replacement. After your six- week post-operative appointment, recommended exercises include walking, swimming, golf, hiking, treadmill walking, stair climbers, light aerobics, weight training, and elliptical exercise equipment.

How active can a person be after a total hip replacement?

You can be as active as you want, and lift as much weight as you desire. Heavy impact exercises, such as basketball, football, soccer, and tennis are probably best avoided, since they contribute to increased prosthesis wear. Low-impact aerobics, bicycling, treadmills, swimming, and similar exercises are fine. Climbing, hiking, and other outdoor activities can be performed as tolerated.

Strength and endurance will build up over time. Modern total hip implants are very durable and designed to take repetitive impact loading for many decades, even in active and heavy patients.

When can I ride a lawn mower, tractor, horse, bicycle, or ATV?

Defer these things for one month after hip implant surgery. You may feel like you can handle such activities sooner, but there is no point in rushing things.

When can I go back to work after surgery?

It depends on the type of work. If you are in hard labor, it is best to wait for three months before swinging into full action. Prior to that time, you can return to some light duty work if this is possible.

For jobs that require some standing, sitting, and walking, it is possible to return earlier. It really depends a lot on the individual and the job. Typically, most people will give themselves at least 3 to 4 weeks after joint replacement before returning to work in some capacity, but some people have returned to work after just two weeks.

When can I drink alcohol after surgery?

Moderate, social alcohol use can be resumed anytime that you wish. Avoid alcohol while you are on any blood thinner or pain medication.

When can one resume sex after a hip replacement or resurfacing?

You can resume sex as soon as comfortable, and in any position that does not cause discomfort. With earlier hip replacement methods, certain restrictions and precautions applied, but these do not apply to modern hip replacements.

How soon can I travel?

As soon as you are comfortable with sitting down, you can travel by airplane or car; there is no specific time period. If you travel, be sure to exercise your calf muscles and ankles frequently. Also, get out of the car or walk the aisle of the airplane frequently to avoid the possibility of blood clots. Continue taking blood thinners while you travel during the first month after surgery.

How long does it take to feel normal after a hip replacement?

A great deal of the recovery takes place in the first two months, but complete return to normal takes longer. Bone around the metal parts keeps changing and remodeling for 1 to 2 years after surgery, which is why you can feel deep aches and can tell when the weather changes. After that time, the hip will feel normal.

Do you use a machine to move the hip after surgery?

No benefit has been shown from the use of continuous passive motion (CPM) machines in hip replacement. Some surgeons use such machines after knee replacement, but they are not needed following hip replacement.

How much can I lift after hip replacement?

You can lift as much weight as you can comfortably tolerate. Once tissues have healed, lifting, climbing ladders or stairs, getting up on roofs, and related activities are safe. Avoid these things for about three months after surgery, until we are sure that your bone has healed into the implants.

Mobility Tips

Tips on walking

The therapist will demonstrate proper and safe walking after a hip replacement, with the use of crutches or walker. The purpose of the walker or crutches is to avoid a fall or sudden twist. Weight-bearing is safe immediately after surgery. But until the implants have grown into the bone, a process that takes 4 to 6 weeks, a fall or other sudden twisting force on the leg can risk implant loosening or injury to the leg. Reflexes take time to return, and narcotic pain medications can further dull the senses. That is the reason for learning to use an assistive device as long as necessary after surgery.

The assistive device can be a walker, crutches, or a cane in either hand; as long as you feel confident and safe in balancing yourself and minimizing the risk of a fall. When using a walker, lean forward, and lead with either leg. When using crutches, avoid putting weight into the armpits; the proper technique is to load the arms as much as needed for a comfortable stride. When using a cane, the most bio-mechanical advantage comes from holding the cane on the side opposite the replaced hip.

Assistive devices can be discarded anywhere from 1 to 4 weeks after surgery, depending on a number of factors, such as narcotic use, return of strength, confidence in walking, return of reflexes, and patient preference. Patients recover differently from each other, and there is no harm in using an assistive device to help in walking for a longer or shorter duration. Because the hip replacement components are designed to heal directly to bone without use of bone cement, the skeletal stability of the implants is assured by 4 to 6 weeks, at the minimum. Around that time, the assistive devices can be discarded, in favor of normal walking in nearly all cases

Tips on stairs

The ability to go up and down stairs requires strength and flexibility. At first, you will need a handrail for support and will be able to go only one step at a time. Always lead up the stairs with your good knee and down the stairs with your operated knee. Remember, “up with the good and down with the bad.” In other words, going up stairs, lead with the good (non-surgery) leg, and coming down stairs, put the bad (surgery) leg down first.

You may want to have someone help you until you have regained most of your strength and mobility. Stair climbing is an excellent strengthening and endurance activity.

Do not try to climb steps higher than the standard height (seven inches) and always use a handrail for balance. As you become stronger and more mobile, you can begin to climb stairs foot over foot.

Managing pain & discomfort

Should I apply ice or heat to the hip as it is healing?

After surgery, and for the first two weeks, ice is more effective in reducing swelling and pain. After complete healing of the skin has occurred, you can use a moist heat pack if it feels comfortable. Soaking in a hot tub at this point may also be helpful.

Whom should I call for pain pills?

Please call the doctor’s office for pain medicines. State regulations allow some medicines to be phoned in; others require a written prescription. Please plan ahead, since narcotic prescriptions on weekends or Friday afternoons can be difficult to call in, mail in, or otherwise get filled.

How long can I have pain medications refilled?

Most patients will taper off the use of narcotic pain medications very quickly. Be aware that some narcotics cannot be phoned into pharmacies. If you will need refills over a weekend or holiday, be sure to contact medical staff during regular office hours.

Some patients require pain medications for a longer time, while others do not need them at all. Your physician will individualize treatment for every person.

How long should I take pain pills?

Most patients use pain medication for anywhere from 1 to 3 months. After three months, you should taper off and begin anti-inflammatory medicines and other non-addictive medicines for pain.

When taken over a long period of time, narcotic drugs create a tolerance that makes them less effective. That is why it is preferable to taper off narcotic drugs quickly after surgery, unless there are compelling reasons to continue use.

What if I need narcotics three months after surgery or if I have been taking them before surgery?

In such cases, the doctor who was filling the prescriptions prior to surgery may resume dispensing the medication. Very rarely, referral to a pain specialist is necessary for patients who are dependent on long-term narcotics.

If you were taking narcotics regularly before surgery, pain control is usually more difficult and complicated since the body is desensitized to the pain control medicines we use after surgery. In such cases, let your doctor know what you are taking before surgery so that they can adjust pain medicines accordingly.

Life with an artificial hip

How long will the artificial hip last?

In most cases, the hip replacement should outlast your lifespan. The 15-to-20-year data on the longevity of hip replacement components is excellent, with more than 90 percent of the implants still functioning well in many studies. But, this is neither a guarantee nor assurance, for the simple reason that life is unpredictable.

Many factors affect the future of a hip replacement or resurfacing, such as accidents, fractures, late infections, and deterioration in your overall health. How well you take care of yourself down the road is something the surgeon cannot control.

The longevity of a hip replacement thus depends on many factors, including the following:

  • Surgeon skill in implanting the components
  • Known history or track record of the implants
  • How well you take care of yourself and your health
  • Understanding and respecting the limitations of a prosthetic lifestyle
  • Your activity level and body weight
  • Avoiding high-impact or extreme sports

How do I know if I have a metal allergy to the hip part?

Orthopaedic implants are made of alloys of cobalt-chrome and titanium that have been implanted in millions of patients over the past several decades. Most instances of a persistently painful hip after replacement have to do with a problem related to the surgery, or possibly an infection. A true metal allergy is extremely rare, and seldom encountered in clinical medicine.

What will weather changes feel like in the hip?

Some patients report increased pain and stiffness, or can feel changes in the weather after hip surgery. These sensations are not common though, and usually will disappear over 1 to 2 years after surgery. For the first couple years, the bone adapts and grows around the metal prosthesis, and this bone activity probably leads to sensitivity to weather and pressure changes.

How about future dental work and other surgery?

Because you have an artificial hip joint in place, you must take care to protect it from infection. The same applies to any artificial implant in your body. Before having dental work (teeth cleaning, fillings, extraction or root canals) or certain medical procedures (colonoscopy, biopsy, endoscopies, etc.), you must take an antibiotic.

The antibiotic will help prevent bacteria from getting into the blood stream and thus into your hip. The odds of this happening are very rare, but the antibiotic can reduce this already small risk.

For routine dental prophylaxis following hip replacement surgery, antibiotics are recommended for your lifetime after the surgery.

In what other situations will I need antibiotics after the hip replacement?

Antibiotics given for other medical procedures may vary. Contact your medical professional for advice if there is any doubt. Antibiotics are needed if you develop an infection such as an abscessed tooth, pneumonia, bronchitis, and skin or urinary infections.

If you have a cut anywhere that develops an infection, conditions like a tooth abscess or ingrown toenail developing, seek medical attention urgently. Ignoring a festering sore means that there is a risk the bacteria could migrate to the hip, resulting in a serious deep infection, even though it happens rarely.

Will the new hip set off a metal detector at the airport?

Most likely, it will. Tell airport personnel that you have an artificial joint prior to entering the metal detector. Metal detection sensitivity at airports is highly variable, and it is impossible to say if a certain detector will set off the equipment. You will be given an implant identification card that you can carry to prove that you have metal hip replacement parts.

Can I have a MRI scan after hip replacement?

Yes. MRI scans of other parts of your body are safe after hip replacement. Although some old MRI scanning equipment may not be compatible with your prosthesis, the majority of MRI scanning equipment today is safe and compatible with hip replacement parts. You may also have a CT scan of any part of your body after a hip replacement.

How will I know if my hip implants are recalled?

In the extremely unlikely event of a recalled implant, you will be contacted by the company who made the device. All implants have lot numbers registered with the implant maker. This information is kept in your medical record. If you want a copy of your X-ray or exact implant type and model for your records, please let your doctor know.

Rest assured that of the millions of artificial joints implanted each year, the incidence of recall is exceedingly rare. Implant companies monitor the performance of their products very carefully.

Is there a long-term risk of failure of hip implants?

Implants are engineered to withstand your body weight and activity level, but the moving parts of a hip replacement do wear over a period of several decades. A properly aligned hip replacement done by a competent, experienced surgeon will usually last the lifetime of most patients.

Subtle component mal-positioning and suboptimal orientation can however compromise the lifespan of the implant. This is why the skill and expertise with which the hip is implanted in your body is a critical determinant of durability.

Filed Under: About Hip Replacement, Featured, HIP, hip surgery Tagged With: blood clots, home, infection, metal allergy, movement, post-op, swelling

Arthritis and the Knee Joint

by

What is a degenerative knee joint?

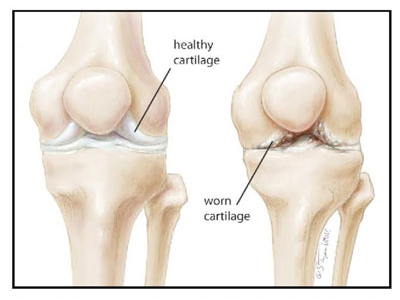
illustration of healthy and worn knee cartilage

As cartilage gets rough, the friction in the joint increases. The result is an inflamed knee joint that swells and hurts. Arthritis and injury are usually responsible for degenerative changes in the knee. Pain, leg deformity, and disability can get severe enough so that patients seek help.

Why does cartilage get damaged?

Cartilage can be damaged by injuries, overuse, inflammatory conditions (like gout, rheumatoid arthritis, and others), and genetic causes. Obesity, poor joint alignment, age, and repetitive trauma to a joint can also damage cartilage. Diseased cartilage loses its smooth, friction-reducing surface, leading to progressive roughening of this biological bearing.

What causes the painful and annoying symptoms of arthritis?

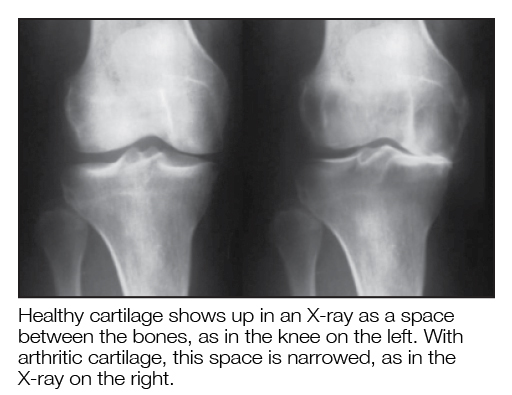
When bone touches bone in the knee joint after loss of cartilage, the result is pain, grinding, swelling, and stiffness. The pain comes from inflammation in the tissues lining the knee joint; inflammation comes from abnormal movement and friction. This is why anti-inflammatory medicines such as aspirin and ibuprofen can often help arthritic pain, at least early in the disease. Swelling and fluid on the knee are adaptive mechanisms by which the body tries to deal with an inflamed and arthritic knee joint.

Is the wear of knee cartilage inevitable with old age?

Not particularly. Even though everything wears with time, the knee joint wears differently from person to person. Most people will never need knee surgery regardless of age. Others are at increased risk of developing arthritis.

While family history, racial origin, and genes may play a role in this, there are things you can do to manage an arthritic knee. Establishing a routine of light aerobic exercise, maintaining ideal body weight, and avoiding extreme sports that injure the knee are some steps that will help reduce the risk of wear in the knee.

Filed Under: KNEE, Knee Surgery Tagged With: arthritis, cartilage

After Knee Surgery

by

Recovering from Knee Surgery

When you’re considering knee surgery, you probably have many questions about post-surgery care. This informative article should address many of your concerns. Don’t hesitate to ask the members of your medical team for their advice and procedures.

What can I expect during the hospital stay?

You can expect several professionals to see you and help you with recovery. A physical therapist will help with knee exercises and walking with an assistive device, such as a walker. An occupational therapist will help you with everyday activities, such as dressing and bathing, while your knee is recovering. Your surgeon will see you often, as will a primary care doctor. Nursing staff will attend to your daily needs, ensuring that the doctor’s instructions are carried out and that you are comfortable. A nursing assistant will help with bathing and activities that you are unable to do yourself.

As you can imagine, the first night or two may be difficult; the hospital environment is new, the bed is not your own, and you will have multiple medications in your system. If you have trouble sleeping in the hospital, please ask the nurse for a sleeping pill. Expect to take a nap during the day, and anticipate several weeks before your normal sleeping patterns are restored, even after you go home.

How long will I be in the hospital?

Most patients are in the hospital for two to three days after a routine knee replacement; some need a longer duration of stay. A social worker will communicate with your insurance about the expected length of stay, and the duration approved by the insurance carrier. The social worker will help with discharge planning.

Preventing Blood Clots

What measures are taken to reduce the risk of blood clots?

Many physicians routinely use a blood-thinning medicine such as warfarin. This drug, or an alternative blood thinner, will be taken for about two weeks after surgery to lower the risk of a blood clot. The hospital pharmacist will monitor the blood-thinner dose, and will advise you if there is any change in the dosage.

After leaving the hospital, you will have a blood test twice a week, or more if necessary, to monitor the efficacy of the blood-thinner.

In addition, the exercises, foot pumps, lack of a tourniquet, efficient surgery, and early walking after surgery all serve to minimize the risk of blood clots. Most physicians use this type of multi-modal program to reduce the risk of blood clots forming.

What more should I know about blood clots?

Any surgery increases the risk of blood clot formation. Some patients are genetically predisposed to clot formation and are at a higher risk. If you have ever had clots in the past, please be sure to let your doctor know.

Clots can cause serious problems such as heart or vascular disease, or a stroke. A lung injury can occur if the clot migrates to your lungs from the leg. A large enough clot migrating to the heart or lungs can be fatal.

Anti-coagulation (blood-thinning) therapy is recommended after all knee replacement operations to reduce the likelihood of developing a clot. Even if a clot develops in the leg, if you are on a blood-thinner, the risk of the clot enlarging and migrating to the lungs is reduced. Exercises, spinal anesthetics, early mobilization, intermittent foot pumps, and blood-thinning medications are all aimed at reducing the risk of blood-clot formation after surgery.

What should I know about the blood-thinning medicine that I will be given?

At present, the most common blood thinner used after knee replacement is the drug warfarin. It is an inexpensive medication that requires adjustment on the dosage for each patient.

You will take warfarin at the same time each day. The dose will be based on a blood test that measures how fast your blood clots. The results are recorded as PT (prothrombin time) and INR (international normalized ratio); the pharmacist will look at these test results and figure out how much warfarin you should take. The goal of taking warfarin is to keep your INR between 1.8 and 2.5. If you miss a dose of warfarin, take it as soon as you remember, but do not double the next dose.

Many things, such as diet, other medications, physical activity and illness can affect warfarin dosing. Vitamins, over-the-counter remedies, herbs, nutrition supplements and other alternative treatments also affect warfarin, and should not be taken while you are on warfarin.

Are there risks to taking a blood-thinner?

Yes, and the obvious risk is bleeding. By thinning blood, we increase the risk of bleeding (something that can be managed), and decrease the risk of clot formation (which can be lethal). Thus, there is a trade-off in risks. The risk of bleeding is common to all blood thinners.

Drugs sometimes used instead of warfarin include heparin and aspirin. Some people may not be able to take warfarin; in that case it’s common to use a drug called enoxaparin. After about 10 days of warfarin, or enoxaparin, doctors typically switch patients to twice-daily aspirin; this combination is safe.

Side effects of warfarin and enoxaparin include dizziness, headache, weakness, cuts from shaving/injury that do not stop bleeding, nosebleeds, bleeding of the gums when brushing your teeth, vomiting blood, bruising or skin rashes, dark brown urine, red or black color to stools, unexpected vaginal bleeding, or unusual pain or swelling. If any such symptoms appear, we may have to switch to a different blood-thinner.

Warfarin interacts with many drugs, both prescription and over-the-counter. Special caution should be given to anti-inflammatory medications such as aspirin, ibuprofen-containing drugs; naproxen, ketoprofen, cimetidine, ranitidine; and food supplements that contain vitamin K.

Supplements, such as ginkgo biloba and danshen also interact with warfarin. Some herbal teas have tonka beans, melilot (sweet clover), or sweet woodruff in them, which contain vitamin K. In addition, foods containing fat substitutes such as olestra are supplemented with vitamin K.

Because so many dietary items affect warfarin, it is essential to monitor the action of this drug two or three times every week with blood draws that are done by the home health agency while you recover at home.


Preventing Infection

How do you prevent infections during knee replacement?

Scrubbing of the skin with an antiseptic, antibiotics given before surgery, surgeon experience, a team-approach designed to promote efficiency, and standardized protocols are some of the key steps in reducing the risk of infection. It is impossible to completely eliminate this risk, but it’s possible to get the risk down to nearly zero. It is very rare to have an infection after routine knee replacement.

Is there a long-term risk of infection in an artificial knee?

Yes, there is a lifetime risk of infection with any artificial implant in your body, whether a knee joint, heart valve, or other synthetic component. As long as you maintain good health and appropriate body weight, avoid smoking, maintain proper hygiene, keep diabetes under control, and promptly address even minor infections in your body, the risk of infecting an otherwise well-functioning knee implant is very low.

What if an infection does develop?

An early infection shows up as redness and pain around the healing incision. This can usually be treated with oral antibiotics alone, usually taken for five to 10 days. Very rarely, as a precaution, the knee joint has to be opened up and washed out to clean the tissues and effectively treat an early infection. This usually happens if the knee starts draining fluid after surgery, which is a rare occurrence.

A late infection that happens months or years after surgery is more serious, and will require additional surgery.

In these rare cases, the infected prosthesis is removed and a temporary antibiotic-loaded knee is implanted, to allow the patient to walk and function, while the infection resolves. After three or more months, a new knee joint is implanted. Six weeks of antibiotics and these two operations will effectively treat an established deep infection in the knee.

Fortunately, deep infections after knee replacement surgery are very rare, usually occurring in immune-compromised patients who have other serious medical problems.

Swelling

How long will I have swelling and warmth in the surgical site?

Swelling and warmth around the scar are common after a knee replacement operation. The ankle may also swell on the operated leg. This represents the normal process of healing and can last for several weeks to months, depending on factors such as circulation, body weight, diabetes, and other variables.

Obesity, diabetes, poor circulation, poor muscles, varicose veins, high activity, heart disease, and swelling before surgery will usually result in a longer period of swelling and heat in the operated leg. Elevating your leg at night and wearing compression stockings during the day will help.

Deep aches and swelling in the knee can persist for a long time because bone, a living tissue, continues to re-model and adapt around the metal implants. This increased metabolic activity can lead to lingering soreness and swelling after heavy activity, all of which will disappear with time.

Leaving the Hospital

What is the average length of hospital stay?

The length of hospital stay after knee replacement varies from just one day to five or more days. There is no standard formula; each person and each recovery is different. Typically, a routine knee replacement requires two to three days in the hospital; there is little to be gained by trying to accelerate this process. People need time to heal.

How is the discharge from the hospital handled?

During your hospital stay, a case manager will work with your doctor to plan your discharge, whether to your home, a skilled nursing facility, in-patient rehabilitation facility, or nursing home. A social worker may also visit, and work with the case manager to formulate a discharge plan.

What determines when I can go home after knee replacement?

You can go home when you are able to get into and out of bed; walk up to 75 feet with a cane, walker, or other assistive device; go up and down stairs; and get to the bathroom. Typically, you will have had a bowel movement before discharge, and will be able to take a shower. Your doctor is the one making the ultimate decision about the safety and timing of your discharge. You will need someone to drive you home from the hospital.

How will I manage at home?

After knee replacement surgery, you will need help at home from an adult family member or friend. If this is not possible, it may be necessary to stay at an inpatient rehabilitation facility. You will not be able to drive for the first couple of weeks.

A home health agency will check on you at home, about three times a week or more, to help with walking, exercise, incision checks, medications, and communication with the doctor. The home health agency will provide a nurse to do blood draws and follow-up care, a physical therapist to continue therapy, and possibly an occupational therapist. The nurse also communicates with your doctor to give regular progress updates.

While at home, if a concern arises, please contact your medical team.  If there is a worry about the incision, taking a digital photo and sending it by email works very well.

When do I have to come back to see the doctor after knee surgery?

You will return for a visit about one month after your operation. If you have problems or questions before then, do not hesitate to call or e-mail your physician. Your home health nurse is also an excellent resource. Patients coming from far away can communicate by e-mail, send digital photos of their incisions and digital X-rays the same way; this works very well and saves a lot of driving and time.

Under what circumstances should I contact a doctor?

It is advisable to contact your surgeon’s office office if you have any of the following:

  • Temperature above 101 degrees
  • Drainage from your incision
  • Excessive redness around the incision
  • Increase in the incision pain
  • Increased leg swelling
  • Pain and swelling in the calf of the leg
  • Numbness or tingling down the back of the operative leg
  • Any other concern, even if it seems minor
  • Your family doctor may be your closest resource for advice if you develop a cold, flu, nausea, vomiting, diarrhea, or constipation. If you are unsure which doctor to call, call your surgeon.

If you cannot reach a doctor and feel that there is a problem, please go to the nearest emergency room. It is best to be vigilant and not take chances.


Common Sensations

Why do I hear a popping noise in the new knee?

Clicking, popping, and other noises in the knee alarm many patients. These are the harmless result of synthetic joint surfaces contacting each other and are common to all prosthetic knee components. The sounds may change over time, may disappear entirely, or may persist. The noises of an artificial knee joint will take some getting used to.

Why are my appetite, mood, food-taste, and sleep different after knee replacement?

Altered appetite, bowel habits, depression, and mood swings are common after any major elective surgery, including knee replacement. This is very important to know, understand, and anticipate. In some cases, medications might be necessary to control such symptoms.

All surgery elicits powerful psychosocial and physiological responses from the patient and vary from one person to another. These responses are normal, and we will help you get through them. It takes time for the body, mind, and soul to recover from any invasive operation.

Why is the outside of my knee numb?

This is normal after all knee surgery. The incision cuts small nerve fibers that run from inside to outside of the knee, so the skin to the outside of the cut always feels numb after knee surgery. Usually, this sensation will resolve over time and is not a major problem for patients. Most patients will not notice that the outside of the scar feels numb.

Is it normal for the muscles to spasm and tighten after surgery?

Yes. Sometimes unexpected spasms of the leg muscles occur after surgery, usually as the person is healing from the operation. These spasms will go away. If they are particularly troublesome, we can prescribe a muscle relaxant medicine, which can help.

Will my leg be longer after knee replacement?

Not noticeably, since it is not possible to lengthen or shorten a leg after knee replacement surgery. The reason is that blood vessels and nerves behind the knee present a practical limitation. Some patients say that the leg feels slightly longer. This comes from straightening out a crooked leg, which ends up feeling longer as a result. The sensation disappears as the patient gets used to having a normally aligned leg again.


Caring for your Incision

How long is the scar for knee replacement?

In most cases, a four- to five-inch incision is enough for knee replacement surgery. Your surgeon will use the shortest possible incision length. Incision length ultimately depends on each patient’s disease severity, anatomy, and amount of body fat.

Many orthopaedic implant companies have developed special instruments to assist in making shorter incisions, and provide training on their effective use. The general rule is to make the incision as short as possible, without compromising the accuracy, precision, or safety that is required for a successful long-term outcome. Since each patient is different, incision length can vary from person to person, even though the same type of knee replacement implants may be used.

Who will remove the staples from the incision?

For the first month, a home health nurse will visit you to check the incision, do blood work to monitor the blood thinner, and help you exercise and walk. That person should remove stitches no earlier than 21 days (three weeks) after surgery.

If there is any question about healing, it is safer to wait another week before removing stitches. Home health nurses can take a digital photo of the incision if there is a concern and send it to your doctor via email.

The preferred method to remove staples is to remove every other one, and apply adhesive-reinforced tape strips to ensure the skin stays together. If there is any concern about the skin edges coming apart, the rest of the staples can be left in for another week; delayed healing can occur in patients with a history of poor wound healing, cancer, diabetes, obesity, and other factors.

Please share this information with the home health person if there are any questions about staple removal. It is safe to shower anytime after staples are removed. Immersion of the incision in bath water, or in a pool should wait till the skin is fully healed.

Can I put any lotion on the scar?

While the staples are still in, it is best not to apply anything to the incision, and to keep the wound clean and dry. Once the staples are out, you can use vitamin E cream to massage and loosen up the scar. Most patients find this beneficial, and some feel that it makes the scar less visible. Massaging the knee area with an anti-inflammatory or cortisone cream can also help reduce skin inflammation and tenderness after knee surgery.

When can I shower after knee replacement?

You can shower as soon as you want after surgery. The incision will be covered with a plastic dressing, and the nursing staff will assist you. If the wound dressing gets wet, you can change it after the shower and use a towel to dry the skin around the incision. Showering reduces the bacterial load on your skin. Once the staples are out and the skin is dry, you can soak the knee in a bath also, but do not soak the incision area in a bath before the staples are removed.


Getting Moving

How long will I be off my feet after knee replacement?

After Knee Surgery

You can put full weight on the replaced knee right after surgery. The therapist will get you up and walking the day after surgery. You will need the assistance of a walker or crutches, but putting weight on the knee and twisting is safe. Most patients are reasonably independent after four weeks, although individual recovery times will vary.

Will I need a walker, crutches, cane, or other assistive device?

Yes. You will likely require a walker for some time after knee surgery. If you have a walker, bring it with you to the hospital. If you do not have one, we can arrange for a walker while you are in the hospital.

Prior to surgery, you should pick up all throw rugs and secure extension/electrical cords at home, and make sure your furniture is arranged to allow you to use a walker safely, without the risk of falling. You can transition to a cane or crutches at any time you are comfortable.

I have pain and stiffness in the first few steps, then the knee feels OK. Is this normal several weeks, or even months after knee replacement?

Yes. Muscles, tendons, and ligaments take time to stretch and accommodate after surgery. The pain that is worse after sitting and goes away with walking is called start-up pain, and can persist for a long time. These symptoms will decrease as tissues heal. An anti-inflammatory medicine can help.

Will I have to learn how to walk again?

Considering that a prosthetic knee has no nerves and that the arc of movement after knee surgery will vary from before, many people feel like they must learn how to walk again. This is to be expected after knee replacement surgery. Take your time, and do not rush the process. There is no point comparing your recovery to anyone else, since recovery is very individual and depends on many patient-specific variables. At some point in your recovery, the new knee will begin feeling like a part of your body. Until then, it is true that you are, in a sense, learning to walk again.

How much therapy will I need?

You need a minimum of four weeks of therapy, usually at your home, with a visiting home health nurse. This person will see you about three times a week. Some patients need therapy after this four-week period, and others are already independent. If you need outpatient therapy, usually four to six weeks will suffice. Once you learn basic knee exercises, you will be able to do them at home.

Maintaining a regular program of exercise and mild aerobic activity long-term is an excellent idea, and you will maximize the benefit of your new knee.

Can I kneel after having a knee replaced?

Yes, although it may take several months before you can do it comfortably. The reason is that the kneecap experiences heavy loads during knee bending; loads that exceed your body weight. Soreness may keep you from kneeling after knee replacement surgery. You can safely kneel as soon as you are comfortable; you cannot damage the knee replacement by kneeling.

What happens if I do not get motion back in the knee quickly?

With minimally invasive surgery, lack of a tourniquet, and minimal muscle disruption, knee motion returns very quickly after replacement surgery. In very few cases, if the knee is not gaining mobility, it may be necessary to manipulate the knee joint under an anesthetic to “fast-forward” you in therapy, and break up early scar-formation in the knee joint. This is rarely necessary, and performed only on individuals who form heavy scar tissue.

Why does scar tissue form in the knee joint?

Scar formation is normal after all operations. After knee replacement, scar formation inside the joint is usually overcome by knee movement. Because of genetic factors and other variables, some patients will form scar very quickly inside the knee joint. Such patients may need additional or more aggressive therapy, and such patients will find that their recovery of knee mobility takes longer than others. This is normal, and again emphasizes that no two patients recover alike since patient anatomy and physiology vary from person to person.

How much bending will I get in the knee joint after replacement?

Implants bend safely to 150 degrees, which is about the physiologic limit of human knee anatomy. Existing scar tissue, contractures of the knee joint, severity of arthritis, pain tolerance, motivation for exercise, body size, and other variables profoundly affect how much mobility a person will get. For most patients, zero degrees of knee extension (bringing the knee out straight) and about 125 degrees of flexion (bending) are easily achieved; this is more than enough for almost all activities of daily living.

Do you use a machine to move the knee after surgery?

No benefit has been shown from the use of continuous passive motion (CPM) machines. Most surgeons use them now out of habit, or because some patients prefer them. If you would like a machine to move your knee after surgery, discuss it with your medical professional. Usually, outcomes from knee replacement are just as good without these machines. CPM machines are never a substitute for using your own muscles and motivation to regain mobility.

Should I exercise after knee replacement?

Yes. A regular program of light aerobic exercise is best, with weight training added to the exercise regimen. Exercise is beneficial from many standpoints, and will optimize the outcomes of your knee replacement. Recommended exercises include walking, swimming, light aerobics, golf, treadmill, stair-climbing, weight-training, and elliptical exercise equipment.

How soon will I be able to return to everyday activities?

Soon after surgery, you will begin to walk short distances in your hospital room and perform everyday activities. This early activity aids your recovery and helps your knee regain strength and movement. A nurse or therapist will assist you as necessary.

Returning to regular activity in terms of walking, exercising, and work vary greatly between patients; most patients return to their regular activities in six to 12 weeks.

How active can a person be after a total knee replacement?

You can be as active as you want and carry as much weight as you can tolerate. Heavy impact exercises, such as basketball, football, soccer, and tennis are probably best avoided, since they contribute to increased prosthesis wear. Low-impact aerobics, bicycling, treadmills, swimming, and similar exercises are fine. Climbing, hiking, and other outdoor activities can be performed as tolerated.

Strength and endurance will build up over time. Modern total knee implants are very durable and designed to take repetitive impact loading for many decades, even in active and heavy patients.

When can I drive after knee replacement surgery?

For the left leg and an automatic transmission in your car, drive whenever you can comfortably sit in a car and have control of the operated leg. For the right leg (and left in the case of driving a car with a clutch), it takes about two to four weeks before you regain the confidence and control in the leg to drive. Of course, you should not drive if you are taking narcotics that make you sleepy or reduce alertness. Avoid driving any time comfort or pain is an issue.

How much can I lift?

You can lift as much as you are comfortable doing. Start out with small weights, and build up your tolerance. As long as the knee does not hurt, lifting weights is fine.

Can I ride horses after knee replacement surgery?

Yes, once your recovery is such that you are independent, strong, and comfortable, you can ride horses, ATVs, and bicycles, with reasonable precautions that apply to each.

When can I go back to work after knee surgery?

The faster you get back to work, the better it is for you, psychologically and physically. We can accommodate your requests for time off work and your return to limited duties. Each individual and job situation is different. Your medical team will work with you to expedite your transition back to your job. Some people with desk jobs have returned to limited work in two weeks after knee replacement; others have preferred to take several months off.

Can I climb ladders?

Yes, climbing ladders is fine as long as the knee is fully healed and your strength has returned.

When can I resume sex?

You can resume sex at any time after knee surgery that you feel comfortable. Unless specifically instructed otherwise in very selected and unusual cases, there are no precautions to follow after knee replacement surgery.

When can I travel after surgery?

Whenever you feel comfortable, go ahead and travel by car or airplane. It is best to avoid the same seated position for over an hour, so try to get up and move around when possible. Otherwise, make sure to do ankle and calf exercises every hour to keep the blood pumping and avoid the possibility of blood clots forming. Prolonged sitting will also cause leg swelling, so it is best to change position during travel if possible.

When can I drink alcohol after surgery?

Moderate, social alcohol use can be resumed anytime that your appetite dictates. Avoid alcohol if your blood is too thin on the warfarin, and your warfarin dose is being held. Heavy alcohol use after any surgery is dangerous.

How long does it take for me to feel normal after a knee replacement?

While 80 to 90 percent of recovery is usually over by the first two months, the last 10 percent can linger. Even though patients can resume normal activities, the bone around the new implants will keep remodeling in response to the altered biomechanics. As a result, it can be up to two years or so before an artificial joint really feels like your own. It can take that long for the skeleton to accommodate the new knee, and feel normal.

Why is recovery after knee replacement said to be harder than after hip replacement?

One, the hip has more muscles covering it, and fewer nerves.

Two, the hip joint is relatively simple, consisting of one kind of movement (ball and socket).

Three, hip surgery can be done even less invasively than knee replacement using modern techniques.

Four, after a hip replacement, very little exercise is necessary for recovery, since there is little risk of the hip getting stiff. In contrast, the knee is a complex joint, relying on outside ligaments for support. These ligaments get stretched with every step. There is very little muscle cover around the knee, so that any bump is felt in the joint.

Finally, the knee tends to scar and stiffen quickly, and the joint must be moved actively to prevent this, and regain motion. For these reasons, recovery after hip replacement is typically a lot easier than recovery after knee replacement.


Helpful Tips

Tips on Walking

Proper walking is the best way to help your knee recover. At first, you will walk with a walker or crutches. Your surgeon or therapist will tell you how much weight to put on your leg; in most cases full weight is safe right away.

Stand comfortably and erect with your weight evenly balanced on your walker or crutches. Advance your walker or crutches a short distance; then reach forward with your operated leg with your knee straightened so the heel of your foot touches the floor first.

As you move forward, your knee and ankle will bend, and your entire foot will rest evenly on the floor. As you complete the step, your toe will lift off the floor and your knee and hip will bend so that you can reach forward for your next step. Remember, touch your heel first, then flatten your foot, then lift your toes off the floor.

Walk as rhythmically and smoothly as you can. Don’t hurry. Adjust the length of your step and speed as necessary to walk with an even pattern.

As your muscle strength and endurance improve, you may spend more time walking. You will gradually put more weight on your leg. You may use a cane in the hand opposite your surgery and eventually walk without an aid. Early on, it is best to moderate the exercise and avoid overdoing it.

When you can walk and stand for more than 10 minutes and your knee is strong enough so that you are not carrying any weight on your walker or crutches (often about two to three weeks after your surgery), you can begin using a single crutch or cane. Hold the cane or crutch in the hand opposite the side of your surgery. You should not limp or lean away from your operated knee.

Tips on Stairs

The ability to go up and down stairs requires strength and flexibility. At first, you will need a handrail for support and will be able to go only one step at a time. Always lead up the stairs with your good knee and down the stairs with your operated knee. Remember, “up with the good” and “down with the bad.” In other words, going up stairs, lead with the good (non-surgery) leg, and coming down stairs, put the bad (surgery) leg down first.

You may want to have someone help you until you have regained most of your strength and mobility. Stair climbing is an excellent strengthening and endurance activity.

Do not try to climb steps higher than the standard height (seven inches) and always use a handrail for balance. As you become stronger and more mobile, you can begin to climb stairs foot over foot.


Managing Pain and Discomfort

How much pain can I expect?

With modern surgery, pain can be controlled very well. Even though modern pain medicines are very effective, some aching and soreness in the knee may persist for many months. This is part of a normal recovery, as long as you notice steady improvement.

Each patient will recover differently; even two knees replaced in the same patient on the same date will recover differently. For example, effective pain control may be a problem for patients who take narcotics regularly before surgery. In these patients, pain relief can be hard to attain since the body desensitizes itself to narcotics.

Will there be persistent pain after surgery?

No, although pain perception varies greatly among patients and the time to full recovery is highly variable. The important thing to watch for is a steady decline in the level of discomfort; the knee should feel better month-to-month. If there is persistent pain, or increasing pain, then further inquiry is necessary. Remember, there will always be patients who go home in a day or two, and never seem to have any pain after knee replacement. There are others who recover far more slowly. The important thing to remember is that both types of recovery are entirely normal.

Should I apply ice or heat to the knee as it is healing?

After surgery, and for the first two weeks, ice is more effective in reducing swelling and pain. After complete healing of the skin and removal of staples, you can use a moist heat pack if it feels comfortable. Once healed, soaking the knee in a hot tub helps, too.

Whom should I call for pain pills?

Please contact your doctor’s office for pain medicines. State regulations allow some medicines to be phoned in; others require a written prescription. Please plan ahead, since narcotic prescriptions on weekends or Friday afternoons can be difficult to call in, mail in, or otherwise get filled.

How long should I take pain pills?

Most patients use the narcotics that are sent home with them for anywhere from one to three months. Over time, they taper off and begin anti-inflammatory medicines and other non-addictive medicines for pain by three months.

Narcotic drugs taken over a long time creates a tolerance that makes them less and less effective. That is why it is preferable to taper off narcotic drugs after three months, unless there are compelling reasons to continue use. This is a general observation; some patients will require narcotic medications for a longer period of time.

What if I need narcotics three months after surgery or if I have been taking them before surgery?

In such cases, the doctor who was filling the prescriptions prior to surgery may resume dispensing the medication. Very rarely, referral to a pain specialist is necessary for patients who are dependent on long-term narcotics. These medications are carefully monitored and tracked in the pharmacy databases, and specialized pain doctors are better trained and equipped to monitor their long-term use.

If you were taking narcotics regularly before surgery, pain control is usually more difficult and complicated since the body is desensitized to the pain control medicines we use after surgery. In such cases, let your doctor know what you are taking before surgery so that we can adjust pain medicines accordingly.

There are no hard rules. Your medical team is there to help you; they understand that every person is different and that pain is very individual.

Filed Under: About Knee Replacement, Featured, KNEE, Knee Surgery Tagged With: blood clot, infection, pain, recovery, scar, swelling, warfarin

Treating Knee Arthritis

by

Can exercise be helpful for knee arthritis?

Yes. Exercises to stretch and strengthen the quadriceps muscles and hamstrings are helpful in reducing the pain of arthritis. Stronger muscles and weight loss will decrease the mechanical loading of the knee joint, resulting in pain relief.

Walking, swimming, light aerobics, elliptical exercisers, and other related activities can be very useful. In some patients, a physical therapist can help design an exercise program to help an arthritic knee. Any exercise is far better than no exercise. Exercise will not make arthritis worse, and will not accelerate the wear and tear in the knee.

Does weight loss help with knee arthritis?

Yes. Excess body weight is multiplied across the knee joint. Thus, gaining 10 pounds of body weight can lead to a 30-pound load on the kneecap, making getting up, climbing stairs, and squatting very difficult.

Losing weight takes load off the cartilage, and decreases the burden on your knees. Weight loss also makes surgery safer. Generally speaking, weight loss and the maintenance of proper body weight can help reduce the pain of knee arthritis.

Does using a cane help with knee arthritis?

Yes, it does. Similarly, using a walker or other assistive device can help by off-loading the knee joint and reducing the tendency to limp. Most people would rather not use a cane, but using one will help with the pain of an arthritic knee.

Will a brace help with knee arthritis?

It depends. Over-the-counter knee braces can be very effective at controlling pain and giving you more confidence and balance in the knee. More expensive custom braces are rarely necessary. Wrapping the knee with an elastic bandage can also relieve arthritic pain.

What other non-surgical steps can I take to relieve pain of knee arthritis?

When possible, avoid stairs and concrete floors, lifting weight, deep bending, twisting activities such as golf, and repetitive impact such as jogging. These are all reasonable, non-surgical options that people use to relieve the pain of an arthritic knee until they are ready for surgery.

Will alternative therapies like supplements and acupuncture help?

Some patients find relief by using over-the-counter remedies like glucosamine, vitamins, oils, shark cartilage, herbal supplements, etc. Such remedies often lack scientific proof of their beneficial effects; be sure to read and understand the package label.

Chiropractor manipulations, acupuncture, massage, heat packs, prolotherapy, aqua-therapy, and related alternatives may also help. Explore and use these options if you feel they are of value. Of course, you should stop any therapy or manipulation that increases your pain.

One important note: If you are scheduled for surgery, stop all herbal, vitamin, and alternative medications at least 10 days before surgery, to avoid excess bleeding and interactions with anesthetics.

Do knee injections help?

Cortisone injections placed in the knee joint can provide relief; the duration of relief varies from patient to patient, often depending on how worn out the knee is. Most patients will get a month or so of relief after a cortisone injection; others may get longer-lasting relief.

Lubricant injections can be given weekly over three to five weeks; these replace the normal knee lubricants. Modern versions of these injections allow for one injection that is given every three to six months or so.

For arthritis that is not quite bone-on-bone yet, these injections can help, and allow patients to enjoy life without having the knee replaced.

Exciting new techniques are always being researched. For example, a new-generation of gold nanoparticles with low-grade radioactivity was used in research to come up with injections that can help with arthritic pain relief for a long time.

How long can I rely on medication as treatment for my arthritic knee?

It depends. Anti-inflammatory medications such as aspirin, ibuprofen, and others in this class of drugs are not addictive drugs. As long as your primary physician is aware and monitors your kidney function, these medications can be taken, within the safe dose range, for many years, even on a regular basis.

Alternative medicines such as glucosamine chondroitin might also help with knee pain. These medicines may not work for everyone, but they are worth a try; in some cases, they can help considerably.

Narcotic drugs are more risky and can create dependence. Also, long-term use of narcotics before surgery makes pain control after surgery more difficult. If your knee pain has progressed to the point where you require narcotic medication, it may be time to think about surgery.

Why not just replace my knee instead of trying non-surgical treatments?

Surgery should be the last option. No knee operation can ever restore the complexity and superior function of your own knee. Surgery also has risks. Experience shows that patients who wait and exhaust all other options before knee surgery have the best outcomes.

Those who rush into surgery without all the information are often unhappy afterward. That is why any responsible surgeon will work with you to try all non-surgical options first. Never rush to surgery, and never bypass other methods of obtaining pain relief.

Does arthroscopic surgery help in the treatment of knee arthritis?

arthroscopy of the knee joint

For some patients, yes. Knee arthroscopy can help by providing several years of pain relief. Such cases usually involve early knee arthritis that has caused a cartilage tear.

Arthroscopy is an outpatient surgery where two or three holes are made in the knee for a camera and instruments that can remove arthritic debris, loose pieces, tears, and related pathology. Sometimes, injections and physical therapy are necessary after knee arthroscopy.

The key value of arthroscopy, in selected cases, is the ability of the surgeon to get a first-hand view inside the joint. This information is not usually available by other methods, and can be useful in planning treatment and understanding the prognosis.

If the cartilage destruction is severe, however, arthroscopic surgery is unlikely to help, and a knee replacement may be indicated.

Are there non-implant surgical options to treat arthritic knees?

In young patients with non-inflammatory arthritis of the knee joint that is not yet extensive and in whom leg deformity is significant, an osteotomy can be done to realign the leg.

This procedure involves cutting bone and realigning the axis of the leg, similar to wheel alignment in a car, to take off the wear from inside or outside the tires. Only a few patients are candidates for such joint-conserving procedures, and we can advise you if you are such a candidate.

When should knee replacement be considered?

The right time to consider knee replacement is when pain pills, exercise, weight loss, bracing, ice, heat, injections, and various alternative therapies no longer provide sufficient relief from the pain of an arthritic knee.

Knee replacement offers dramatic pain relief and increased motion. Some soreness and stiffness will persist for weeks to months in a few patients, but ultimately most people are glad they had surgery.

If pain, swelling, grinding, deformity of the leg, and decreased ability to function are severe enough to get your attention, and non-surgical options have not worked, it may be time to consider replacement surgery.

Filed Under: Arthritis and the Knee Joint, KNEE

About Hip Replacement

by

Hip Replacement FAQ

Hip replacements should not be undertaken lightly; below are some of the most common questions patients have.

What is a total hip arthroplasty?

Surgeons use the word “arthroplasty” to mean replacement. The word “total” means that both the ball and socket part of the hip are replaced. “Total hip arthroplasty” means the same thing as total hip replacement.

Is there a partial hip replacement?

Yes. In some cases of hip fracture in elderly patients who have no arthritis in the joint, surgeons may elect to replace only the ball. This means a metal ball moves inside the patient’s own socket.

In low-demand patients, this is a reasonable option, although a total hip replacement is usually more durable and offers more predictable pain relief (see illustration).

When should hip replacement be considered?

The ideal time for surgery is when other measures, such as medicines, exercise, weight loss, and alternative therapies no longer work. If hip pain causes a limp, affects your lifestyle, interferes with work or recreation, and negatively impacts your body image, then surgery is a reasonable option.

Will a new hip joint be a perfect substitute for my own hip?

Metal and plastic cannot fully replicate the complexity, intricate engineering, and healing ability of the human body. Hip replacement components are products of modern science and engineering that come close but cannot duplicate the natural hip joint.

However, a prosthetic hip provides dramatic pain relief and improves movement, function, and lifestyle. Many patients experience complete resolution of their pre-surgery pain and discomfort.

How does the artificial hip joint get lubricated?

The replaced hip develops a lining around it, and the cells secrete synovial fluid (a biological lubricant) into the synthetic joint. This fluid provides lubrication so that the artificial bearing is never dry.

Synovial fluid is recycled by the cells. No external lubrication of the new hip joint is ever needed. Injections into an artificial hip joint are not beneficial and will increase the risk of infection.

About how long does a hip replacement take?

It varies – a common time is about half an hour. However, patient preparation for surgery, safe positioning, safety checks, and anesthesia add considerably to this time. Individual patient and anatomic variations may also alter surgical times. Each person is unique and surgery is never an assembly-line procedure.

Is it possible to replace both hip joints at the same time?

Yes. This has become routine when patients need both hips replaced and are in good health otherwise. Rehabilitation time is perhaps slightly longer than for one hip replacement, but not noticeably so.

Many surgeons use the “anterior” surgical approach to hip replacement, which means that the patient is on his or her back, and muscles are spread, rather than cut. This usually makes surgery on both sides much simpler, safer, and faster.

Ask your surgeon about their surgical approach; new procedures are always being developed and refined to improve recovery and minimize surgery needs.

What is the optimal age for hip replacement?

Hip replacement is usually done in patients in their 50s through their 80s, although the operation is also done in patients who are older or younger than this age range. With modern implants and bearings, young age is not a contraindication to successful surgery. In the past, hip replacement was reserved for the elderly, because the implants and synthetic bearings were not as durable as they are today.

Should I wait, or get my hip replaced now?

The availability of new technology, streamlined surgical methods, and improved implants should not rush your decision to have a hip replacement. Non-surgical methods of relieving pain should be tried first; sometimes they can help postpone surgery for many years. A reasonable period of waiting and careful decision-making is always wise.

Will waiting to get a hip replacement make things worse?

No. Waiting is safe. Even if the hip joint gets becomes more deformed, the surgery is just as easy. The only downside to waiting is that muscles might get weaker and more stiff, thereby making recovery a bit longer. This can be offset by maintaining a reasonable body weight and following a program of light exercise to keep your muscles in shape.

One exception applies to revision hip implant surgery. If your joint was replaced many years ago, and the wear particles are starting to dissolve bone, your physician may advise you to have surgery sooner rather than later.

Another exception applies to joints that have been replaced, and are suspected of having a deep infection of the prosthetic device. In those cases, corrective surgery is recommended early, so that the infection does not penetrate the bone.

How many joints can one have replaced?

About Hip ReplacementIt is possible to have multiple joints replaced safely. For patients with other serious health conditions, it may be best to get these done one at a time, starting with the worst one first.

Some patients do have more than a single hip or knee replacement; it is not unusual for people to have artificial joints in both hips, knees, shoulders, and more. The ability to replace painful joints is a remarkable advancement in medicine.

What if my previous hip replacement surgery did not work out?

Hip surgery can be complicated by deep infection, implant mal-positioning, nerve injury, leg length discrepancy, and other unhappy outcomes. A second opinion is worth exploring even if a surgeon tells you nothing can be done.

Many factors can compromise the results of hip replacement, even though the X-rays look fine. A step-by-step approach to identifying the reason for an unsatisfactory outcome, and addressing it, can help patients who have had a poor outcome.

Hips can be replaced more than once. Modern technology allows replacement of deficient bone, even if the entire femur bone is lost.

Where else can I learn about hip surgery?

To learn more about the anterior hip replacement technique specifically, visit newhipnews.com. Another useful source is bonesmart.org, which even has a patient dialogue forum. Manufacturers of hip implants have patient education websites as well.

Can arthritis occur in a hip after it is replaced?

Replacement surgery eliminates all diseased cartilage in the hip joint. It is not possible to have arthritis since the native cartilage is gone and will never grow back.

However, arthritis is a complex disease that affects tissues around the joint, such as nerves, muscles, ligaments, and the synovial lining of the hip. This is why some pain, stiffness, and internal swelling can persist for many months even after X-rays show complete healing following a hip replacement.

Muscles and tendons, weakened and stiff from years of disuse, can take 1 to 2 years to stretch and adapt after hip surgery.

Will hip replacement get rid of all my pain?

Yes, if all the pain is really coming from the hip joint. But an artificial hip cannot relieve pain coming from an arthritic spine, weak muscles, arthritic knees, hernias, poor circulation, fibromyalgia, rheumatoid arthritis, and other such conditions.

How long is recovery after hip replacement?

Most recovery is in the first 4 to 6 weeks. By then, bone grows into the metal components and most patients become mobile enough to walk without a cane.

During the first 4 to 6 weeks, be cautious and use a walker or cane while walking, and avoid sudden twists and falls. Eight weeks after surgery, most patients can resume light lifting and other daily activities.

Very heavy lifting, returning to strenuous jobs, and extended exercise should wait until three months. These timeframes are approximate; healing varies from patient to patient.

The bone around the metal implants continues to adapt and remodel for 1 to 2 years after surgery. During that time, expect some mild aches and pains, and discomfort with pressure and weather changes. Ultimately, all such sensations will resolve.

Is recovery from hip replacement faster for younger patients?

No, not necessarily. The recovery appears to be more or less the same for young and older patients with hip arthritis. The recovery from hip replacement also seems to be very similar between men and women, as well as between thinner and heavier patients.

Is recovery faster after hip replacement than knee replacement?

Yes, people recover faster after hip replacement, with less pain and less need for physical therapy, when compared to knee replacement. There could be several reasons for this.

The knee joint is more complex, and involves many different types of movement; the knee may have more nerves transmitting pain sensations; hips have a heavier protective layer of muscle and tissue compared to knees, and there may be other explanations why recovery from hip replacement is usually easier than a knee replacement.

Patient perception between a knee replacement and a hip replacement is also different. It can take a couple of years, or longer, for an artificial knee to feel natural and like the real thing. In contrast, a hip replacement feels natural, and more like the real thing after considerably less time.

What are the inherent risks of hip surgery?

Inherent risks are those complications that can occur, no matter where you have surgery done, or who performs it. You should know these in order to make an informed decision about surgery.

No hospital, physician, or surgical method can eliminate the inherent risks associated with hip surgery; beware of any hospital or surgeon who claims otherwise.

Complications after hip surgery are rare, typically occurring with a frequency of 1 percent to 2 percent of the cases. Each complication listed below is discussed in more detail, elsewhere on this website. If you prefer to discuss this in person, please ask your physician.

Possible adverse outcomes after hip surgery include, but are not limited to, blood clots, pneumonia, nerve injury, blood vessel injury, blood transfusion risks, anesthetic complications, heart attack/cardiac complications, stroke, failure of implants, dislocation of the components, superficial or deep infections, bone fracture, leg length inequality, and even death.

How much does a new hip joint cost?

Insurance contracts, hospital pricing, medical billing, and other variables related to cost are complex. In fact, specially trained personnel are required to do medical billing. If you want to know the costs involved, please contact your physician’s office; their billing team will give you an accurate answer.

Will Medicare or my insurance cover hip surgery and therapy?

Yes. However, insurance plans and related benefits vary; to be certain, it is best that you check with your insurance company. Talk to your medical team as well, since surgery and hospital stays must be pre-authorized with insurance companies.

Filed Under: Featured, HIP, hip surgery Tagged With: arthroplasty, artificial hip, hip joint

Diagnosing Knee Arthritis

by

Arthritis of the knee is a common underlying cause for knee replacement surgery. Here’s what you should know.

How is worn cartilage diagnosed?

Symptoms such as pain, swelling, stiffness, lack of movement, and grinding in the knee can suggest that knee cartilage is no longer smooth. X-rays are a common way of diagnosing diseased cartilage in the knee. The X-rays show the bones around the joint. The cartilage layer cannot be seen on X-rays, and shows up as a space between the femur and tibia bones.
x-ray comparison of healthy and arthritic knee cartilage
In a healthy knee, this space is about a quarter of an inch thick. When joint space taken up by cartilage is destroyed by arthritis, X-rays will show joint-space narrowing. With significant cartilage loss, the bones may touch each other; doctors call this finding “bone-on-bone” on the X-rays.

Over time, cysts and bone spurs may form around the knee. Left untreated, the leg can get so deformed that it appears to be either bow-legged or knock-kneed.

Are there other ways to see the extent of damage to knee cartilage?

MRI scans are a special X-ray study that can diagnose diseased cartilage somewhat more accurately and at an earlier point than plain X-rays. Another method includes actually looking inside the knee during a procedure called “knee arthroscopy.” This involves the surgeon placing a small camera in the knee and inspecting the cartilage.

Filed Under: Arthritis and the Knee Joint, KNEE Tagged With: arthritis

Before Knee Surgery

by

Health Considerations Before Knee Surgery

When you’re getting ready for a knee operation, here are some important things to know, especially since knee surgery has possible complications.

What do I need to do to prepare for knee surgery?

Reading the information on this site, communicating with your surgical team, and paying close attention to the checklists will best help you prepare for knee replacement surgery. The importance of preparation and information to successful surgery cannot be overemphasized.

What health conditions must be considered before undergoing surgery?

Some patients have unusual problems, such as HIV infection, hemophilia, cancer, bleeding disorders, liver or kidney transplants, enzyme disorders, and other conditions that require specialty consultations before surgery. If these considerations apply to you, your medical team will work with you to obtain the necessary testing and treatment prior to surgery.

What medical testing is needed prior to knee replacement surgery?

Before Knee SurgeryPre-surgical checks are essential for your safety and it is unwise to short-circuit them; they are comparable to pre-flight checks that every responsible pilot makes before taking off. Out-of-town patients, or those traveling long distances, can have local doctors perform these checks. Usually, your medical team will work with your doctors to expedite this.

The typical pre-surgical checks are listed below; your doctor may include others.

Medical Check: Prior to your surgery, you should see an internal medicine specialist to identify and manage your health risks. Examples of increased risks are heart and lung disease, tooth and gum disease, infection, obesity, and diabetes. That is why patients should undergo testing and clearance by a medical doctor prior to knee replacement surgery.

Dental Check: A dental check-up is necessary to identify any hidden infection in your teeth or gums. Such infections must be treated before knee replacement to eliminate the risk that bacteria from decayed teeth enter the bloodstream and end up infecting the knee implants. If you are traveling from out of town, visit your dentist and forward the information to your surgeon.

Heart Check: If there is any reasonable suspicion of heart disease based on your history, it is best to find out ahead of time if your heart is healthy enough for knee replacement surgery. Heart disease is usually silent; patients do not have symptoms until the heart is stressed. If indicated, you will be asked to see a cardiologist before surgery for clearance.

What if I have bowel problems?

Pre-existing trouble with constipation usually leads to constipation and related problems after knee replacement. If you regularly take supplements to encourage bowel movements, let your doctor know so they can plan accordingly, since medicines used during and after surgery can result in serious constipation.

You will be given a stool softener before surgery to avoid problems with constipation later. Even so, you can probably expect disturbance of bowel patterns and at least some degree of constipation after knee replacement surgery.

How does diabetes affect my surgery?

Blood glucose levels over 200 will lead to poor wound healing and increased risk of infection. Therefore, it is critical that your diabetes is under control prior to surgery. A medical consultation and lab data before surgery will help your team to ensure your diabetes is controlled and your surgical risk is minimized.

Does osteoporosis affect the success of a total knee replacement?

No. If bone has severe osteoporosis, it may not be possible to use an un-cemented prosthesis. However, the cemented version of total knees can be implanted in nearly every type of bone, including bone that has osteoporosis, and the outcomes are very successful.

What about alcohol and drug use?

Regular alcohol consumption should be disclosed to your anesthesiologist and surgeon ahead of time. Alcohol withdrawal can happen to anyone, regardless of economic or social background. When it happens, it can be life threatening and can complicate your recovery from surgery. If your physicians know about alcohol consumption, they can take steps to avoid withdrawal. The same is true of recreational drugs. Be sure to talk about this with the anesthesia doctor.

What if I am a smoker?

Smoking increases the chance of lung complications during and after surgery, delays wound healing, increases the risk of complications after surgery, and increases the odds of residual knee pain even after successful knee replacement. Therefore, you should try to stop smoking, both for your general health, and to improve the odds of a successful result from knee replacement. Most hospitals are smoke-free, and you may not be able to smoke on the premises.

Does my body weight affect knee replacement?

Obesity will increase the risk of complications from surgery, such as blood clots and slower wound healing. Ideally, your weight should be within reasonable limits before knee replacement surgery. In some cases, for excessively heavy patients, knee replacement is not an option without drastic weight reduction, such as with gastric bypass surgery.

That said, many people are somewhat overweight and unable to lose weight while dealing with a painful arthritic knee. The knee components are designed to handle enormous loads, and are safe, even in very heavy people. There is no evidence to suggest that the components loosen up prematurely, or wear out prematurely in heavy people.


Exercise Before Surgery

What about dieting and exercising before surgery?

Maintain a nutritionally sound diet including a variety of foods in preparation for surgery. Crash dieting is not necessary; rather, regular exercise will help control weight and improve overall health.

Exercise before surgery, done within reason, and within the capability of the patient, will improve the recovery from knee surgery. Therefore, a reasonable exercise program to strengthen your thigh and calf muscles before knee replacement surgery is the best thing you can do to speed up your recovery.

How can exercise before the surgery help my recovery after?

Exercising and strengthening the thigh and leg muscles before the operation will result in faster recovery and return to function, with less suffering, struggle, depression, and mood swings. Consultation with a physical therapist before surgery can be very useful.

The reason exercise helps is that the knee, even if worn out, is a living joint. Living tissues respond positively to physiologic stress, and exercise is known to improve self-perception, esteem, and outlook.


Preparing for the Hospital

When do I first visit the hospital?

About a week or so before surgery, you will visit the pre-op department in the hospital. This visit is to read and sign consents for the surgery, for the anesthesia, and for blood products (if needed). You will have lab tests, possibly a chest X-ray, and an electrocardiogram. Please make a list of your medications and their dosages prior to this visit.

At this visit, you will be instructed on where to report on the morning of surgery. You will receive instructions on not eating or drinking after midnight the night before your surgery. This includes chewing gum and hard candy.

Keep in mind that surgery schedules change often; this is why the exact timing of the operation is not known until the day before. If you have a special preference, such as being the first in the day, or last, or in between, simply let the surgeon know and they will do their best to accommodate.

When will I be assigned a surgery time?

The hospital will contact you a day before the surgery to tell you what time to arrive at the hospital. Surgery schedules tend to change, which is why most hospitals will confirm the exact surgery time only a day or so before the operation. Please arrive early. The actual operation will usually be less than an hour in duration, but preparation takes much longer.

When do I see the anesthesiologist?

On the morning of your surgery, you will see an anesthesia doctor (anesthesiologist) who will have already reviewed your medical records. If your medical condition so requires, your surgeon will have consulted with the anesthesia doctor ahead of time. This doctor will inquire about your health and plan the anesthetic technique, including any regional nerve pain blocks. If you know of a particular anesthesiologist at the hospital whom you would prefer to provide this service, simply let someone on your medical team know ahead of time.

Should I donate my blood for surgery?

No. This is not necessary since not everyone needs a blood transfusion after knee replacement. If you have religious convictions against blood products, let your doctor know so they can arrange to recycle your own blood. Blood loss differs from patient to patient, and pre-existing conditions such as anemia and other diseases can affect the odds of needing blood after surgery.

As a general rule, major bone surgery is associated with blood loss, but it is impossible to say how much blood a particular patient will lose. If needed, blood transfusions today are very safe and effective.


Preparing for the Return Home

Do I need someone to stay with me after surgery?

If you live alone, an adult friend or relative should stay with you, in addition to the home health nurse visits during the week. For very elderly patients and patients with other health problems, a stay in a rehabilitation unit or a nursing facility may be necessary.

You might consider local home health agencies prior to coming to the hospital. If you have private insurance, you will need to make sure you choose a home health agency contracted with your insurance. The best time to do this is before you have surgery. Ask your doctor about these resources; they can arrange many of these things for you to ensure a smooth transition to your home.

How long do I need someone to stay with me after surgery?

You should plan on about two to four weeks, depending on your individual circumstances and available resources. During the first month, a home health nurse will visit you several times a week. Having someone with you can help with daily activities and chores, even though you will be able to walk and transfer yourself by the time you leave the hospital.

Where can I get a disabled parking sticker?

Your doctor should have forms that allow you to get a temporary disabled parking placard. A permanent disabled placard is not necessary after knee surgery, since the new knee is designed to increase your mobility. Some patients need a few weeks or months of parking in disabled zones, and others do not.

How do I prepare my home for after surgery?

Prior to surgery it is a good idea to take a close look at your home environment to determine if it is “user friendly” for someone on crutches or a walker. Modifications and equipment needs can be addressed ahead of time to ease your return home.

How do I prepare my home for after surgery?

Examine your home environment to see if it is user-friendly for crutches or a walker. Modifications and equipment needs often include the following:

  • Remove loose throw rugs, runners, area rugs in pathways. They can get tied up in the wheels of a walker, catch on a crutch tip or slide when stepped on.
  • Moving furniture to widen pathways and making sure doors open fully will make it easier for you to navigate with a walker or crutches. Bathroom doors are often too narrow to get through. Your physical therapist will instruct you in a safe technique to use.
  • A toilet riser, commode, grab bar on wall, or arm rests that easily attach to a toilet may be helpful as getting up and down may be difficult initially.
  • A step-in shower is the easiest to access. Many have seats built right in. If you have a bathtub only or tub/shower combination, a portable shower chair may be necessary for about a month. Having a grab bar is also recommended for optimum safety. Towel racks are not designed to hold the body’s weight and do not replace a grab bar.
  • Having at least one rail on stairways to provide support is recommended.
  • Night lights are recommended for all pathways used after dark.
  • A portable telephone comes in handy when you are alone at home.

Medication Use Before Surgery

Can my doctor fill narcotics medications until my surgery?

Before surgery, your physician can prescribe medications that are non-narcotic and non-addictive. These typically include anti-inflammatory medications and some light narcotic pain medications.

Any addictive drugs, such as narcotic pain-killers, should be obtained from your primary care doctor before surgery. Your primary care doctor and surgical team should be aware of all your medications, especially narcotic medicines.

When, and what medicines, should I stop?

In consultation with anesthesia and the pre-surgical medical consult, you will be advised personally which medications to stop in anticipation of surgery, and when to stop. The following are some general guidelines:

  • Ten days before surgery, stop taking blood thinning medications, such as clopidogrel bisulfate, ticlopidine, or aspirin, as well as vitamins, nutritional supplements, herbal supplements, fish oil, and anti-inflammatory medications, such as ibuprofen.
  • Five days before surgery, stop taking warfarin. This is a blood thinner that is usually prescribed for conditions such as blood clots, strokes, and irregular heart rhythm.
  • Other medications can be continued until the day of surgery. If you are taking steroids, chemotherapy, or medications for rheumatoid arthritis (such as methotrexate), you will be told when to stop those.
  • If a medication is not listed here, check with your internist or family doctor. You can also discuss these with your surgeon, the anesthesia staff, or the pre-op staff when you visit the hospital. When in doubt, please e-mail or call.

Should I take vitamins and supplements before surgery?

No, and these should be stopped around 10 days before surgery. Vitamins, herbal supplements, and nutrition supplements can interact with the other medicines we use during surgery, and can lead to excessive bleeding during and after surgery. After knee replacement, patients usually take a blood thinner for around a month. You can resume taking vitamins, supplements, and alternative therapies once you are off the blood thinner.


The Night Before Surgery

What do I need to do the evening before surgery?

The evening before surgery take a shower, but avoid shaving the legs, since this increases the bacterial load.

For your hospital stay, pack a bag with a robe or housecoat that opens in the front; house shoes or comfortable shoes for physical therapy; personal hygiene items; underclothing; glasses or contact lenses with case; dentures or partials with case; a case for hearing aid and spare battery; a walker if you have one; a C-Pap machine if you use one; loose fitting clothing to wear for physical therapy; advance directive if you have one; a list of current medications with dosages; an inhaler if you use one; and reading material, cell phone, and laptop computer if you prefer. The hospital has wireless Internet for your use.

Can I take my medicines the night before surgery?

You should take your blood pressure and heart medications with just a sip of water the morning of surgery. Your medical doctor may advise differently; if so, please follow his or her instructions and let the surgical team know. For example, in some patients, warfarin may be an essential medication safeguarding against stroke. In that case, your surgeon will work with the medical doctor to continue this drug, and alter their surgical preparation accordingly.

The pre-operative visit to the hospital is a good time to take notes and ask questions. Each patient is different;  procedures and planning should be customized to your individual needs.

Why might surgery be cancelled at the last minute?

If you have an unexpected health problem, it may be safest to postpone the surgery until the situation is addressed. Let your doctor know if you have any of the following close to your scheduled surgery: symptoms of a cold or flu (chills, fever, or a cough); pain, burning or frequency when you urinate; cuts, scratches, rashes, bug bites, non-healing sores on your skin; new swelling on the leg undergoing surgery; or a change in your medical condition, such as high blood sugar or chest pain. These situations could mean that surgery has to be rescheduled.

Filed Under: KNEE, Knee Surgery Tagged With: checks, hospital, medications, pre-surgery

  • « Go to Previous Page
  • Page 1
  • Interim pages omitted …
  • Page 9
  • Page 10
  • Page 11
  • Page 12
  • Page 13
  • Go to Next Page »

Primary Sidebar

ORTHO NEWS

Spinal anesthesia tied to increased opioid use after hip surgery

Spinal anesthesia tied to increased opioid use after hip surgery

Useful Health Tips for People With Chronic Hip Issues

Useful Health Tips for People With Chronic Hip Issues

A robotic assistant for joint replacement surgery

A robotic assistant for joint replacement surgery

Prior Diagnosis of COVID Has No Increased Complications in Total Joint Arthroplasty

Prior Diagnosis of COVID Has No Increased Complications in Total Joint Arthroplasty

Putting Your Best Foot Forward for Joint Surgery Success | Health

Putting Your Best Foot Forward for Joint Surgery Success

Use of Antibiotic Lavage in Total Knee Replacement to Prevent Postoperative Infection

Use of Antibiotic Lavage in Total Knee Replacement to Prevent Postoperative Infection

Tips to care for an elderly after hip replacement surgery

Tips to care for an elderly person after hip replacement surgery

Exactech Total Knee Failure Resulted in Revision Surgery, Lawsuit Alleges

Exactech Total Knee Failure Resulted in Revision Surgery, Lawsuit Alleges

AAOS Updates Clinical Practice Guideline for Surgical Management of Osteoarthritis of the Knee

AAOS Updates Clinical Practice Guideline for Surgical Management of Osteoarthritis of the Knee

Robotics Procedure Helping People Recover From Joint Replacement Surgery

Robotics Procedure Helping People Recover From Joint Replacement Surgery

Copyright 2014 All Rights Reserved · DISCLAIMER: Nothing here constitutes legal, medical, or other advice; all content relates to an individual perspective only. A professional relationship with a physician, or with a lawyer is built over time, with mutual investment, trust, and respect. This site is not a substitute for that.
~ THIS DOMAIN IS FOR SALE ~

Privacy Policy